

Shoulder impingement
Classification of Shoulder Impingement
Shoulder impingement is categorized according to cause and severity as follows:
- Primary impingement:
- Caused by anatomical changes such as bone spurs or an abnormal shape of the acromion.
- Secondary impingement:
- Due to functional problems, such as instability or muscle weakness.
- Internal impingement:
- Mainly affects athletes and is caused by repeated overhead throwing movements.
Causes of shoulder impingement
The causes of shoulder impingement are varied and include:
- Anatomical changes:
- Bone spurs or variations in the shape of the acromion narrow the subacromial space.
- Overuse:
- Repeated overhead work, such as by painters or craftsmen, as well as sports activities like tennis or swimming.
- Degenerative processes:
- Age-related wear and tear of tendons and bursae, especially of the rotator cuff.
- Muscular imbalances:
- Weakness of the stabilizing shoulder muscles leads to incorrect movement of the shoulder joint.
- Shoulder instability:
- Common in young, athletically active people due to overstretching or injuries.
Symptoms of shoulder impingement
The symptoms of shoulder impingement can vary, but are typically:
- Pain:
- Especially during overhead movements or lifting the arm to the side. The pain often occurs at night or at rest.
- Movement restrictions:
- Difficulty lifting the arm above shoulder height.
- Loss of strength:
- Reduced strength when holding or lifting objects.
- Swelling and inflammation:
- Accompanying signs of inflammation in the shoulder joint area.
- Grinding or rubbing:
- Mechanical noises when moving the arm.
Diagnosis of shoulder impingement
The diagnosis is made through a combination of medical history, clinical examination, and imaging techniques:
- Medical history:
- The doctor inquires about the exact location of the pain, the course of the symptoms, and possible triggering activities.
- Clinical examination:
- Tests such as the Neer test or the Hawkins-Kennedy test help to reproduce the symptoms.
- Imaging techniques:
- X-ray: Visualization of bone spurs or shape changes of the acromion.
- MRI: Detailed examination of tendon tears or inflammation of the rotator cuff.
- Ultrasound: For assessing bursitis or minor tendon damage.
Treatment options for shoulder impingement
Conservative Therapy
Most cases of shoulder impingement can be treated without surgery:
- Physiotherapy:
- Targeted exercises to strengthen the rotator cuff and improve shoulder mobility.
- Medication Therapy:
- Nonsteroidal anti-inflammatory drugs (NSAIDs) to relieve pain and inflammation.
- Injections:
- Cortisone injections into the subacromial space for rapid anti-inflammatory effects.
- Ergonomic Adjustments:
- Avoidance of overhead movements and optimization of the workplace.
Surgical Therapy
If conservative measures are not sufficient, surgical intervention may be necessary:
- Subacromial Decompression:
- Removal of bone spurs and expansion of the subacromial space.
- Rotator Cuff Repair:
- Reconstruction of torn rotator cuff tendons.
- Arthroscopic Procedures:
- Minimally invasive procedures to treat bursitis or tendon damage.
Preventive measures for shoulder impingement
To prevent shoulder impingement, the following measures are helpful:
- Regular training: Strengthening the shoulder muscles, especially the rotator cuff.
- Ergonomic work practices: Avoiding overhead loads and adjusting movement patterns.
- Warming up before sports activities: Preparing the shoulder for stress through targeted mobilization exercises.
- Early treatment of shoulder complaints: At the first signs of pain or movement restrictions, consult a doctor in a timely manner.
Bursitis
A bursitis, also called bursitis, is an inflammatory condition of a bursa, caused by irritation, overuse, or infections. Bursae are small fluid-filled cushions that lie between bones, muscles, and tendons and serve as shock absorbers and sliding…

Rotator cuff tear
A rotator cuff tear refers to damage or a tear of the tendons in the shoulder joint that connect the muscles of the rotator cuff to the humerus. It is one of the most common causes of shoulder pain and limitations in shoulder mobility. The injury can…
Tear of the supraspinatus tendon
A tear of the supraspinatus tendon is a common injury of the rotator cuff and affects the tendon of the supraspinatus muscle, which is responsible for the abduction and stabilization of the shoulder joint. The injury can occur acutely or chronically…
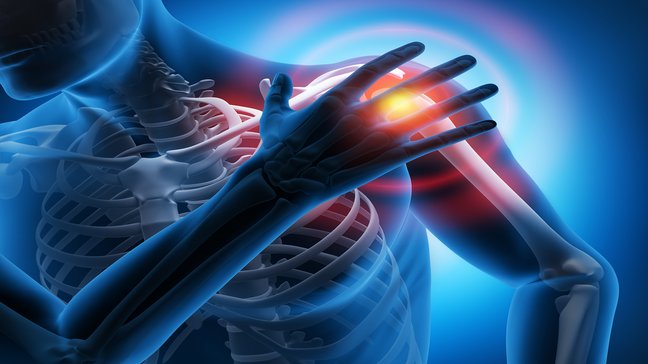
ACG-Osteoarthritis
ACJ osteoarthritis (acromioclavicular joint osteoarthritis) is a degenerative disease of the acromioclavicular joint that can lead to pain, movement restrictions, and chronic discomfort. It often affects middle-aged and older individuals as well as…
Shoulder impingement
Classification of Shoulder Impingement
Shoulder impingement is categorized according to cause and severity as follows:
- Primary impingement:
- Caused by anatomical changes such as bone spurs or an abnormal shape of the acromion.
- Secondary impingement:
- Due to functional problems, such as instability or muscle weakness.
- Internal impingement:
- Mainly affects athletes and is caused by repeated overhead throwing movements.
Causes of shoulder impingement
The causes of shoulder impingement are varied and include:
- Anatomical changes:
- Bone spurs or variations in the shape of the acromion narrow the subacromial space.
- Overuse:
- Repeated overhead work, such as by painters or craftsmen, as well as sports activities like tennis or swimming.
- Degenerative processes:
- Age-related wear and tear of tendons and bursae, especially of the rotator cuff.
- Muscular imbalances:
- Weakness of the stabilizing shoulder muscles leads to incorrect movement of the shoulder joint.
- Shoulder instability:
- Common in young, athletically active people due to overstretching or injuries.
Symptoms of shoulder impingement
The symptoms of shoulder impingement can vary, but are typically:
- Pain:
- Especially during overhead movements or lifting the arm to the side. The pain often occurs at night or at rest.
- Movement restrictions:
- Difficulty lifting the arm above shoulder height.
- Loss of strength:
- Reduced strength when holding or lifting objects.
- Swelling and inflammation:
- Accompanying signs of inflammation in the shoulder joint area.
- Grinding or rubbing:
- Mechanical noises when moving the arm.
Diagnosis of shoulder impingement
The diagnosis is made through a combination of medical history, clinical examination, and imaging techniques:
- Medical history:
- The doctor inquires about the exact location of the pain, the course of the symptoms, and possible triggering activities.
- Clinical examination:
- Tests such as the Neer test or the Hawkins-Kennedy test help to reproduce the symptoms.
- Imaging techniques:
- X-ray: Visualization of bone spurs or shape changes of the acromion.
- MRI: Detailed examination of tendon tears or inflammation of the rotator cuff.
- Ultrasound: For assessing bursitis or minor tendon damage.
Treatment options for shoulder impingement
Conservative Therapy
Most cases of shoulder impingement can be treated without surgery:
- Physiotherapy:
- Targeted exercises to strengthen the rotator cuff and improve shoulder mobility.
- Medication Therapy:
- Nonsteroidal anti-inflammatory drugs (NSAIDs) to relieve pain and inflammation.
- Injections:
- Cortisone injections into the subacromial space for rapid anti-inflammatory effects.
- Ergonomic Adjustments:
- Avoidance of overhead movements and optimization of the workplace.
Surgical Therapy
If conservative measures are not sufficient, surgical intervention may be necessary:
- Subacromial Decompression:
- Removal of bone spurs and expansion of the subacromial space.
- Rotator Cuff Repair:
- Reconstruction of torn rotator cuff tendons.
- Arthroscopic Procedures:
- Minimally invasive procedures to treat bursitis or tendon damage.
Preventive measures for shoulder impingement
To prevent shoulder impingement, the following measures are helpful:
- Regular training: Strengthening the shoulder muscles, especially the rotator cuff.
- Ergonomic work practices: Avoiding overhead loads and adjusting movement patterns.
- Warming up before sports activities: Preparing the shoulder for stress through targeted mobilization exercises.
- Early treatment of shoulder complaints: At the first signs of pain or movement restrictions, consult a doctor in a timely manner.
Bursitis
A bursitis, also called bursitis, is an inflammatory condition of a bursa, caused by irritation, overuse, or infections. Bursae are small fluid-filled cushions that lie between bones, muscles, and tendons and serve as shock absorbers and sliding…
Rotator cuff tear
A rotator cuff tear refers to damage or a tear of the tendons in the shoulder joint that connect the muscles of the rotator cuff to the humerus. It is one of the most common causes of shoulder pain and limitations in shoulder mobility. The injury can…
Tear of the supraspinatus tendon
A tear of the supraspinatus tendon is a common injury of the rotator cuff and affects the tendon of the supraspinatus muscle, which is responsible for the abduction and stabilization of the shoulder joint. The injury can occur acutely or chronically…
ACG-Osteoarthritis
ACJ osteoarthritis (acromioclavicular joint osteoarthritis) is a degenerative disease of the acromioclavicular joint that can lead to pain, movement restrictions, and chronic discomfort. It often affects middle-aged and older individuals as well as…